Heart surgery clinics: compare techniques and specialist teams
Robotic valve repair in Berlin. Repeat surgery in Istanbul. Arterial bypass in Gurugram. Find the differences that matter to your operation.
Research by Yevhenii Kozlov · Co-Founder of BookimedUpdated 8 October 2026Sources linked throughout
At a glance
Compare 25 clinic programmes through the procedure they offer: valve preservation, robotic access, arterial bypass, complex HCM or repeat surgery. Each profile connects the clinical focus to named specialists and research.
Procedure-specific selection
The directory filters hospitals by treatment area rather than treating all cardiac departments as interchangeable.
Photos and named teams
Clinic cards link to the hospital profile and relevant clinicians, with image and clinical sources.
Complete programme comparison
Five treatment programmes expose method, price basis, care and recovery on one page.
The clinical distinctions make it easier to see which programmes address the hardest part of the case, before comparing destination and cost.
Trade-offs and limits
Registry ratings refer to defined procedures and participating groups, not a worldwide league table of every surgeon. Patient reviews describe experience rather than clinical effectiveness.
Aortic-root surgery with a native-valve preservation focus
Pitié-Salpêtrière’s adult cardiac and aortic service lists Emmanuel Lansac on its team. His research on root remodelling with external annuloplasty offers a specific valve-preserving approach to a root aneurysm with or without leakage.
Root and valve treated together Remodelling replaces the diseased root while external annuloplasty supports the valve annulus.
Technique-specific comparative evidence A 375-repair observational study compared 289 dedicated rings with 86 Dacron rings and found fewer late reoperations/leaks with the dedicated ring.
Current service affiliation The official AP-HP service includes cardiac surgeons, cardiologists and anaesthetists treating adult cardiac and aortic disease.
Procedures and specialists
adult cardiac surgeryaortic surgeryaortic valve repair assessmentvalve-sparing root surgery assessment
Complex valve repair and valve-sparing aortic-root surgery
Anadolu in Gebze offers complex valve repair and replacement of an enlarged aortic root while retaining the natural valve. Smaller-incision valve operations and selected robotic mitral or tricuspid procedures are also part of its cardiovascular programme.
Native-valve preservation The programme includes complex valve repairs and valve-sparing aortic-root replacement.
Several access options Selected mitral and tricuspid procedures can use robotic access; minimally invasive valve surgery is also described.
Adult and paediatric scope Haşim Üstünsoy’s institutional profile covers both adult and paediatric cardiovascular surgery.
Procedures and specialists
CABGvalve repair and replacementaortic surgeryminimally invasive valve surgerycomplex valve repairs
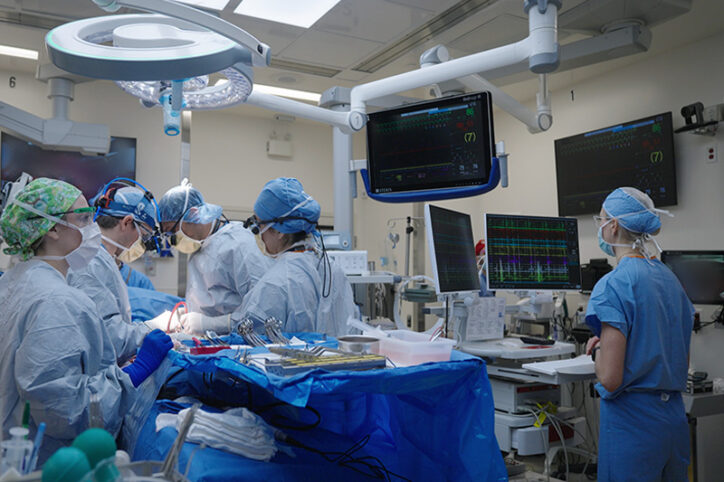
Conduction mapping during biventricular repair at Boston Children’s: the source identifies Elizabeth DeWitt, Eric Feins and Sitaram Emani. Photo courtesy of Benjamin Eckstein/Beryllium Pictures; published January 2025. · Photo source
Complex two-ventricle reconstruction with long-term planning
Boston Children’s Complex Biventricular Repair Program evaluates difficult ventricular relationships using detailed imaging and 3D models. Its research addresses both protection of the conduction system during repair and the later burden of conduit procedures.
Anatomical reconstruction The programme describes tailored outflow and valve reconstruction for unusual ventricular connections.
Conduction mapping evidence A study compared 149 mapped repairs with 201 controls; heart-block/pacemaker frequency was lower in selected anatomical subgroups.
Later procedures can be expected in some pathways In the 25-patient Yasui series, freedom from conduit reoperation was 48% at median five-year follow-up.
What this means for your choiceDetailed anatomical modelling and tailored reconstruction create a two-ventricle pathway for selected difficult congenital hearts.
Surgical and catheter valve treatment within one heart team
Bumrungrad’s Heart Valve Center offers surgical valve repair/replacement together with TAVI and MitraClip assessment. Imaging, cardiac anaesthesia and rehabilitation are part of the same multidisciplinary service.
Surgery and catheter options The service lists surgical aortic replacement, TAVI, mitral repair/replacement and catheter mitral repair with MitraClip.
Imaging before TAVR Its May 2026 pathway describes echocardiography and CT assessment before multidisciplinary treatment planning.
Named care disciplines The valve team includes surgeons, interventional cardiology, cardiac imaging, anaesthesia and cardiac rehabilitation.
What this means for your choiceSurgical and catheter valve options can be assessed in one service with imaging, anaesthesia and rehabilitation disciplines.
Robotic mitral repair measured by anatomy and durability
Cedars-Sinai’s Smidt programme has studied both an expanding robotic team and the durability of complex Barlow repair. Its evidence distinguishes getting a valve repaired from preventing recurrent leakage years later.
Team experience A 1,410-operation registry involved four surgeons; 1,234 of 1,237 degenerative valves were repaired.
Complex anatomy analysed separately The Barlow analysis covered 111 patients within a 924-patient degenerative-mitral registry.
Five-year Barlow endpoint Survival free from greater-than-moderate leakage was reported at 92%, with an 80.2%–98.1% confidence interval.
Teknon’s current CABG package names Xavier Ruyra Baliarda and includes preoperative testing and consultations, an individual room and five hospital days. The hospital also describes his team’s beating-heart and blood-conservation techniques.
Advertised medical package The live programme displays $41,411.97 for CABG, preoperative tests, consultations and five inpatient days.
Specific team capabilities Teknon’s official Ruyra profile describes beating-heart coronary surgery, mini extracorporeal circulation and bloodless cardiac surgery.
Medical and travel costs separated Hotel, airfare and transfers are excluded from the displayed package.
What this means for your choiceThe medical package defines preoperative assessment, room type and inpatient days, with hotel, airfare and transfers transparently excluded.
Distinct teams for mitral repair, HCM and complex valve reconstruction
Cleveland’s cardiac services bring together different expertise: Gillinov’s mitral/robotic work, Smedira’s myectomy practice, Kapadia’s catheter valve treatment and Unai’s endocarditis and redo reconstruction. Its published cohorts show why valve anatomy and supporting tissues can matter as much as the incision.
HCM beyond septal muscle The 2005–2015 series included 522 operations combining myectomy with mitral or subvalvular treatment.
Robotic mitral repair The 2006–2013 series completed 992 repairs in 997 attempts among 1,000 robotic mitral operations.
Catheter and reconstructive pathways Official profiles separately identify Kapadia’s TAVR work and Unai’s endocarditis and complex repeat-surgery practice.
What this means for your choiceDistinct valve, myectomy, catheter and endocarditis specialists support different anatomical problems rather than a single general cardiac-surgery label.
Congenital treatment from defect closure to staged reconstruction
Columbia’s congenital service treats ASD and VSD alongside complex neonatal disease, congenital valve abnormalities and single-ventricle pathways. Childhood care connects to adult congenital assessment within the programme.
Broad defect-specific scope The official service lists ASD/VSD repair, arterial switch, Fallot repair and Norwood/Glenn/Fontan pathways.
Congenital valve expertise Bacha’s profile and the programme identify valve reconstruction and a dedicated congenital valve service.
Early robotic pathway A 26-patient 2023–2025 report involved selected children and adults, mainly with ASD or anomalous pulmonary venous return.
What this means for your choiceThe programme spans isolated defect repair, neonatal reconstruction, congenital valve work and transition to adult congenital care.
Aortic reconstruction, transplantation and mechanical support
Duke combines cardiac and vascular aortic expertise with an advanced heart-failure service. Hughes’s team covers the root through the thoraco-abdominal aorta; Schroder’s surgical remit includes transplantation, LVAD, ECMO and total artificial heart.
Aortic continuity of care The centre describes imaging, genetics and lifelong surveillance alongside open and endovascular treatment.
Repair durability is technique-specific In 71 HAART-ring repairs, 11 patients developed at least moderate leakage at mean 3.9-year follow-up; all had trileaflet valves.
Support and transplant pathways Duke’s advanced heart-failure surgery service includes durable LVAD, temporary ECMO, total artificial heart and transplantation.
Procedures and specialists
aortic valve repairvalve-sparing root replacementaortic arch and thoracoabdominal repairthoracic endovascular aortic repairheart transplantationLVADECMOtotal artificial heartselected surgery with severely reduced LV function
What this means for your choiceAortic disease can be managed across cardiac and vascular disciplines, while a separate service offers transplant and temporary or durable circulatory support.
Robotic valve repair with a structured early-recovery pathway
DHZC in Berlin pairs robotic mitral repair with ERMICS, a recovery pathway linking anaesthesia, pain control and early mobilisation. Its bypass service also describes conventional, beating-heart and selected robotic approaches.
Dated robotic experience DHZC reported more than 260 robotic operations on 12 November 2025 after starting the programme earlier that year.
Recovery starts in hospital ERMICS supports transfer to a regular ward on the day of minimally invasive valve surgery for suitable patients.
Different bypass approaches The coronary service describes conventional surgery, beating-heart bypass and selected robotic options.
Procedures and specialists
CABGoff-pump CABGselected minimally invasive CABGrobotic mitral repairselected robotic CABGheart-valve surgery
What this means for your choiceThe ERMICS pathway connects minimally invasive valve surgery with pain control and early mobilisation; suitable patients reach a regular ward on the same day.
HDZ NRW links cardiac surgery, transplant follow-up and an integrated heart-failure centre. Dedicated VAD coordinators make device support a defined part of the service alongside the implantation procedure.
Specialist device support The department describes VAD coordinators and specialist medical/nursing support for patients with mechanical assistance.
Inpatient and outpatient continuity Its integrated heart-failure centre coordinates care across hospital and outpatient settings.
Right-heart function remains important A 57-patient imaging study found only modest prediction of right-heart failure after HeartMate 3 implantation, supporting assessment beyond one measurement.
Procedures and specialists
heart transplantationmechanical circulatory supportVAD follow-upintegrated heart failure care
What this means for your choiceContinuing VAD support and coordinated outpatient/inpatient care are described parts of the programme, not only the implantation procedure.
Repeat valve surgery and a priced robotic bypass pathway
Hisar combines Ali Fedakar’s stated focus on second and third valve operations with Faruk Gençoğlu’s minimally invasive and robotic cardiac work. Its current robotic CABG offer itemises inpatient monitoring, postoperative follow-up, hotel accommodation and transfers.
Repeat operations Fedakar’s listed interests include second and third valve operations, beating-heart bypass and aortic-dissection surgery.
Robotic CABG programme The Gençoğlu offer advertises Da Vinci bypass and seven hospital days for $20,000 through 6 November 2026.
Postoperative support The package includes nursing, monitoring, medically indicated follow-up tests and travel transfers; airfare is excluded.
Procedures and specialists
coronary bypassbeating-heart bypassminimally invasive cardiac surgeryredo valve surgeryaortic surgery
What this means for your choiceThe service combines explicitly listed redo-valve expertise with a named robotic CABG package that includes postoperative monitoring and travel transfers.
HCM, apical aneurysm and congenital disease with complex anatomy
Mayo Rochester’s surgical scope includes septal and selected apical myectomy, congenital valve reconstruction and repeat operations. Dearani’s practice connects HCM with Ebstein anomaly and paediatric/adult congenital surgery.
Selected apical reconstruction A programme series studied transapical myectomy together with apical aneurysm repair in 67 patients treated during 2000–2020.
Dated follow-up That selected cohort reported estimated five-year survival of 94.5%, with median follow-up of 4.9 years.
Congenital and redo scope Dearani’s profile includes Ebstein anomaly, adult and paediatric congenital surgery and multiple reoperations.
What this means for your choiceThe programme includes pathways for selected apical aneurysm disease and congenital/reoperative problems beyond routine basal HCM obstruction.
Arterial grafts, beating-heart bypass and robotic access
Medanta’s Gurugram team describes different solutions to different CABG decisions. Surinder Bazaz focuses on total-arterial beating-heart bypass and coronary endarterectomy; Nitin Rajput’s scope includes robotic-assisted CABG, endoscopic valve replacement and redo operations.
Graft material Bazaz’s practice explicitly includes total-arterial bypass, using arteries as conduits, on a beating heart.
Access and repeat surgery Rajput’s listing names robotic-assisted CABG, endoscopic aortic/mitral replacement and repeat bypass or valve surgery.
Combined cardiac disease The wider team covers coronary, valve, aortic and complex redo conditions under chief cardiac surgeon Naresh Trehan.
Procedures and specialists
CABGoff-pump and beating-heart surgeryvalve repair and replacementaortic surgeryredo surgeryminimally invasive and robotic surgery
What this means for your choiceNamed surgeons cover separate CABG choices: arterial grafts and diffuse coronary disease, beating-heart support, and robot-assisted chest access.
HCM surgery tailored to the valve apparatus, with emerging robotic access
NYU’s HCM programme combines medical treatment, imaging and surgery. Swistel’s work addresses elongated leaflets and papillary attachments; Scheinerman is named in the hospital’s first reported robotic trans-mitral myectomy. The valve service also includes Kodali’s transcatheter expertise.
Established HCM team NYU names Daniel Swistel as surgical director and Joshua Scheinerman as associate surgical director.
Anatomy-specific surgical history Swistel’s resect–plicate–release work combines myectomy with selected leaflet shortening and papillary release.
A specific robotic report The hospital names Scheinerman, Grossi and Nampi in a robotic trans-mitral case with discharge on postoperative day four.
Procedures and specialists
HCM myectomy with mitral repairtranscatheter tricuspid therapies
What this means for your choiceThe HCM team covers medical and surgical treatment, with anatomy-specific valve-apparatus work and a separately reported robotic route.
Robotic Barlow repair using an anatomy-specific strategy
NewHeart Watanabe’s published mitral work focuses on Barlow disease, a complex form of prolapse. The team used artificial chordae as its first strategy and added leaflet resection when needed to manage systolic anterior motion.
124 Barlow repairs The 2015–2022 robotic cohort included 124 selected patients, with no conversion to valve replacement.
Reported complications The report recorded four bleeding events and one stroke; a small incision did not eliminate procedural risk.
Follow-up beyond discharge Freedom from reoperation was 99.2% during mean follow-up of 36 months.
What this means for your choiceThe published Barlow technique combines artificial chordae and selective leaflet resection to retain a complex native mitral valve.
Bypass graft selection with ten-year randomized evidence
Weill Cornell’s Mario Gaudino explicitly practises multiple arterial CABG, including radial and bilateral internal mammary grafts. His research helps explain the long-term implications of conduit choice independently of a robotic or conventional incision.
Specific graft expertise The official profile names radial arteries and both internal mammary arteries among his clinical interests.
1,036 randomized patients A pooled analysis found fewer deaths, heart attacks or repeat procedures with radial-artery than saphenous-vein grafts at median ten-year follow-up.
Research continues His institutional profile identifies leadership of ROMA and ROMA:Women trials.
Procedures and specialists
CABGmultiple arterial graftingadult cardiac surgery
Total-arterial bypass through a smaller chest incision
Toronto General’s Peter Munk MICS programme, directed by Piroze Davierwala, describes single-vessel and selected multivessel CABG using arterial grafts. The service distinguishes graft strategy, access side and use of heart–lung support.
Three coronary routes UHN describes left-sided direct bypass, right-sided direct bypass and multivessel total-arterial CABG.
Selected off-pump operations The programme describes multivessel arterial bypass without a heart–lung machine in selected patients.
Current Toronto leadership Davierwala is identified as surgical director; his preceding Leipzig experience is documented separately.
Procedures and specialists
single-vessel minimally invasive CABGmultivessel total-arterial minimally invasive CABGminimally invasive valve and aortic surgery
What this means for your choiceSelected multivessel operations combine arterial grafts, a smaller intercostal incision and avoidance of heart–lung support.
HCM myectomy that addresses abnormal mitral chordae
Monza’s HCM work combines muscle resection with correction of selected abnormal secondary mitral chordae. The purpose is anatomical relief of obstruction while retaining the native valve, with longer follow-up than a purely early feasibility report.
350-patient follow-up The 2026 publication studies 350 consecutive patients with median follow-up of 5.6 years.
Reported symptom status Of 344 patients with follow-up, 271 were in NYHA class I and 65 in class II at latest assessment.
A connected heart centre Hospital materials describe cardiac surgery, cardiology, imaging, intensive care and rehabilitation, with a 2026 HCM research update.
Procedures and specialists
HCM septal myectomy with secondary mitral chordal cutting
What this means for your choiceIts studied HCM operation preserves the mitral valve while treating abnormal secondary chordae and septal muscle together.
Valve-sparing root surgery with wider aortic expertise
Royal Brompton’s Ulrich Rosendahl profile includes preserving the aortic valve during root replacement, repair of other valves and surgery on the arch and thoraco-abdominal aorta. Its scope is especially relevant when valve disease overlaps with aneurysm, inherited disease or previous surgery.
Root and native valve Valve-sparing root replacement treats the enlarged root while retaining suitable valve tissue.
Inherited and extensive disease The profile includes Marfan and Loeys–Dietz syndromes, arch disease and thoraco-abdominal aortic surgery.
Repeat reconstruction Repeat heart and aortic operations are stated areas of Rosendahl’s practice.
Procedures and specialists
aortic-root and arch surgerythoracic-aortic surgeryaortic valve surgerymitral reconstructionCABGminimally invasive surgery
What this means for your choiceRoot preservation, more extensive aortic reconstruction and redo expertise are described within the same surgical practice.
Septal myectomy through the apex on a beating heart
Tongji’s HCM contribution is transapical beating-heart septal myectomy, developed by Xiang Wei’s team. The entry point and heart support differ from conventional transaortic myectomy and Cui’s infra-axillary operations.
A named technique developer The current department page names Wei as director and describes the team’s transapical myectomy system.
Separate anatomical cohorts The evidence includes a 418-patient series and an earlier 61-patient study focused on midventricular obstruction.
Beating-heart access The described method avoids cardiopulmonary bypass in the studied operation.
Totally endoscopic CABG, including selected multivessel and hybrid plans
UChicago’s robotic cardiac programme is led by Husam Balkhy and specifically describes totally endoscopic beating-heart CABG. Its published experience includes bypass to several vessels and hybrid treatment combining bypass with stents.
A specific robotic operation TECAB places bypass grafts through ports; the official profile identifies beating-heart TECAB as a principal technique.
544-patient programme series In the 2013–2020 series, 56% had multivessel TECAB, with one conversion to sternotomy and reported mortality of 0.9%.
Subgroup graft assessment Early patency was 97% in assessed patients receiving hybrid revascularization.
What this means for your choiceSelected patients can receive fully endoscopic beating-heart grafts, including multivessel or hybrid bypass-and-stent treatment.
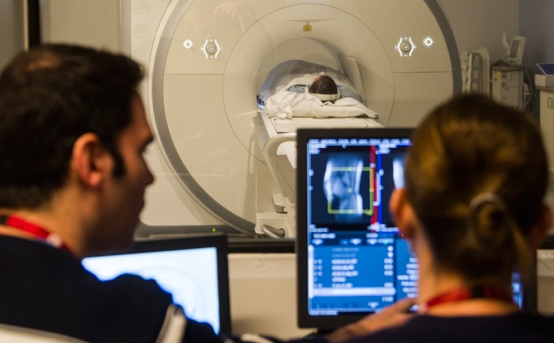
Archive photograph of MRI test scanning at the University of Ottawa Heart Institute, published February 2015. The source identifies the person in the scanner as a staff volunteer. · Photo source
Minimally invasive bypass with recovery and long-term follow-up evidence
Ottawa’s CABG work includes both randomized evidence on the incision and observational evidence on later coronary treatment. The distinction is useful: faster early recovery does not prevent progression of disease in other native arteries.
Measured early recovery MIST randomized 170 patients suitable for both routes; one-month SF-36 physical-component scores averaged 45.1 with MICS versus 42.2 with sternotomy.
Longer-term repeat treatment In a separate 566-patient cohort followed for a mean seven years, 49 underwent repeat revascularization.
Why repeat procedures occurred Progression of native coronary disease was the most frequent reason for further revascularization in that cohort.
What this means for your choiceIts research provides both a measured early recovery benefit in eligible patients and evidence that later coronary disease still needs attention.
WashU’s cardiac service includes minimally invasive atrial-fibrillation and valve surgery. Its historical Cox-Maze IV cohort gives a view of recurrence over years, including patients with persistent AF and previous catheter-ablation failure.
A defined surgical rhythm service Ali Khiabani’s current profile lists minimally invasive AF surgery and valve surgery at Barnes-Jewish.
853 patients in the historical cohort The 2003–2018 series included 60% nonparoxysmal AF and 24% with previous catheter-ablation failure.
Long-term results have denominators Freedom from atrial tachyarrhythmia was 84% of 253 assessed at five years and 77% of 87 assessed at ten years.
Procedures and specialists
surgical atrial fibrillation treatmentminimally invasive AF surgeryvalve surgery
What this means for your choiceA current surgical AF service is paired with long-term institutional rhythm follow-up that includes patients with previous catheter-ablation failure.
HCM surgery through an underarm incision, with the breastbone preserved
The Hangzhou team has published operations that relieve obstructive HCM through an incision near the right armpit. Its newer 100-patient MESM study reports early relief of obstruction while preserving the breastbone. An earlier study also treated abnormal mitral-valve supports that contributed to the blockage.
148 patients in the earlier series The 2024 report covers right infra-axillary transaortic myectomy performed during 2021–2023.
Supporting structures treated Papillary resection occurred in 72 of 148 patients and chordal resection in 93 of 148; some patients received both.
A separate MESM study The newer 100-patient cohort evaluates extended septal sculpting and reports aortic cross-clamping; it is distinct from beating-heart transapical surgery.
Procedures and specialists
published transaortic septal myectomy via right infra-axillary incisionprovider-described trans-axillary minimally invasive valve procedures
What this means for your choiceThe earlier infra-axillary series demonstrates combined septal and subvalvular correction through the same smaller access.
Look for a difference that changes the operation: a repair strategy for your valve, an arterial-graft plan, a way to address difficult anatomy, or a recovery pathway that fits the proposed procedure. The procedure-specific rankings add published case counts and follow-up where available.
Criterion
Why it matters
What you can inspect
Procedure fit
A programme should explicitly treat the condition you have
Official programme and surgeon sources
Named operator and team
A department leader may not be the surgeon assigned to you
Role, clinical interests and the actual proposed team
Comparable outcomes
A result is meaningful only with its population and endpoint
Procedure, year, case mix, denominator and follow-up
Complete care plan
Surgery is only one part of the journey
ICU/rescue capability, rehabilitation and local handoff
Clear commercial terms
Quotes must describe the same scope
Included procedure, nights, medicines and extra charges
What surgical ratings, reviews and accreditation can tell you
STS public reporting is voluntary and covers participating groups in the United States and Canada. Results refer to particular procedure categories and reporting periods. The registry warns against direct participant-to-participant comparisons; the ratings are not a worldwide league table of individual surgeons.
Patient reviews describe experiences. Accreditation describes compliance with an accreditor’s standards. Both may be useful, but neither is a substitute for a procedure-specific outcome discussion.
Our sources, selection criteria and Bookimed’s role
Clinical details come from the hospitals’ current programme pages, named specialists and primary studies. Published results stay attached to their procedure, patient group and date. Bookimed’s coordination service is funded by participating hospitals; this guide also covers specialist reference centres.
Daniel Swistel · Joshua Scheinerman NYU Langone Hypertrophic Cardiomyopathy Program
An HCM team that treats septal and mitral causes of obstruction, with conventional and selected robotic surgical approaches.
Quote on request
Individual estimate after assessment.
NYU reports more than 600 myectomies at programme level. Supporting method evidence includes a historical 77-patient anatomy study and a separate first robotic case report.